Ideas for adding iron rich foods to your child’s diet

Iron Man slippers on a kid who needs to eat more iron-rich food

The comic hero Iron Man may have had a suit of iron, but even his parents probably needed to encourage iron intake. If you are picturing yourself chasing after cows with a fork in order to provide iron-rich foods to your kid, take heart. There are lots of foods which are rich in iron.

Aim for two iron-rich food servings per day.

Surprisingly it’s not meat but iron-fortified cereals that top the list for iron content per serving. 


For babies

Serve oatmeal, rice, barley, or multigrain cereals from the “baby food” aisle: A serving of ¼ cup = 4 Tablespoons contains 60% of a baby’s daily iron requirements- 6.75mg of iron. Prepare the cereal using breast milk or formula for some added iron and other nutrients.

For older kids  

Cheerios: 1 ½ cup = 70% Daily value (assuming a diet of 2000 cal/day) of iron 12.6mg iron

Quaker oatmeal squares: 1 cup contains 90% Daily value (assume 2000cal/day) or 16.6mg

Grape Nuts : ½ cup = 100% Daily value or 18mg iron per serving

Kellogg’s Frosted miniwheats, approx 25 squares = 100% or 18mg iron

If you give cereal, you can use Dr. Kardos’s rule for her own kids, as some iron-fortified cereals also contain too much sugar: if you choose a sweet cereal (more than 8g of sugar per serving), you must mix it half and half with a not-so-sweet cereal.

Help your kids absorb the iron in their food

Assuming  your kids drink cereal with milk, unfortunately calcium in milk inhibits iron absorption. You can change that by serving up some vitamin C containing fruit like strawberries with the cereal.

Be sure to read labels! Just the other day, Dr.Lai was dismayed to find her beloved brand of steel-cut oats, although high in fiber, has very little iron. 

More iron-rich food suggestions

Beef, pork, lamb, chicken, turkey, fish, shellfish- all contain iron. Drink water and not milk with a meat-containing meal to help your kids absorb the iron better. Also, serve a vitamin C containing fruit on the side, such as strawberries, melon, and oranges to boost your child’s absorption of iron.

It is worth highlighting the current trend for  teens, especially boys, to use protein powders. The problem, is that by using powders instead of eating meat, they miss out on eating a rich source of iron. 

Vegetarian kid? Tofu, beans, eggs, fortified rice, spinach, kale, dried fruit all contain iron.

A comprehensive  table of iron content in foods can be found here.

Do you have a picky eater who refuses all iron-rich foods? Ask your pediatrician to recommend an appropriate iron supplement. Iron is important for brain health as well as blood health.

Naline Lai, MD and Julie Kardos, MD

©2026 Two Peds in a Pod®



Food Allergies- Epinephrine hints and a free coloring book

Allergy Coloring Book
For a free electronic copy of a food allergy coloring book, write us at twopedsinapod@gmail.com

As kids head back to school, it’s a good time to review how to administer your food-allergic kid’s emergency epinephrine. Dr. Lai, who has two young adults who grew up with food allergies, and Dr. Kardos offer these hints:

-Double check to make sure the medication has not expired. Also, make sure you are giving the school medication that does not expire in the middle of the school year.Double check to make sure the medication has not expired. Also, make sure you are giving the school medication that does not expire in the middle of the school year.

-What about antihistamine or asthma medications? Yes, go ahead and send them in with your child, but remember, only  epinephrine can  reverse the life-threatening symptoms of an anaphylaxis. Other medicines like antihistamines cannot stop the reaction.


-Be aware that the safety caps on different epinephrine pens can look different. So, open a pen up, examine it, and refresh your memory on instructions for administration.

-Have at least 2 doses available in case one dose is not working, 911 is taking longer than expected to arrive, or something goes awry with administration of a first dose.

-There is a nasal spray form of epinephrine which is under the brand name Neffy. Since it is newer, check with the school nurse whether they are familiar with administration.

How-to video on epinephrine injection as part of a girl scout silver award project-note that some devices have shorter hold times. Be sure to read the directions for your own device.

Naline Lai, MD and Julie Kardos, MD

©2026 Two Peds in a Pod®
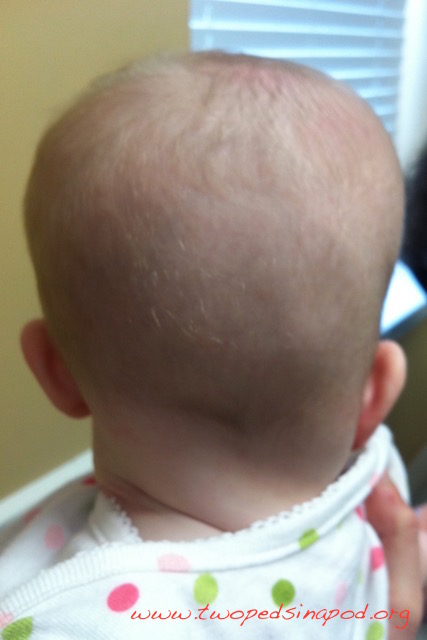


Why do tummy time?

Tummy time can prevent flat head syndrome, or plagiocephaly

Your insta feed is probably flooded with ideas on how to encourage tummy time with your baby. 

We see one pediatrician has garnered nearly a million views. So why bother with tummy time in the first place?

In the late 1990s, pediatricians noted that while the safe sleep recommendation of “back to sleep” prevented sudden infant death syndrome, back sleeping caused the back of heads to flatten. Tummy time gives babies time off of the back of their heads. 

Rest assured, it is not important for your baby to have a perfect basketball-shaped head. Instead, you are helping to prevent obvious flattening. Once your baby learns to sit, around 6 to 7 months, they will spend much less time lying down and have more time for their heads to round out as they continue to grow. 

Flattening from pressure on the skull is called “positional plagiocephaly,” which is different from the more serious condition of  craniosynostosis. Routine pediatrician visits help your baby’s doctor to determine if your baby’s head is growing correctly.


There are other pluses to tummy time. Tummy time develops neck strength and eventually arm strength, which will help your baby as they try to roll over and, later, to crawl.

Three tips for tummy time: 

  1. Just like when you get out of a car after a long drive, everything is a little squished and stiff for a newborn. Even from birth, your baby may have a preference to turn their head to the same side. You can start tummy time while awake as soon as you get home from the hospital.

  1. When awake, tummy time is another alternative to a bouncy seat, a wearable harness, etc. Tummy time lets your baby exercise and interact with their tummy-time vantage point of looking up and around them. 

  1. Babies with older siblings are the most likely to spend time on their backs as their siblings dance around them and their parents have less time to reposition their youngest. We chuckle when the parents of baby number 3 ask us about the shape of their baby’s head and then reply: “Oh yes…tummy time… we forgot about that.”

Naline Lai, MD and Julie Kardos, MD

©2026 Two Peds in a Pod®



Prevent your children from ingesting THC edibles

gummy bears on a dish that look just like edibles

“4 Bucks County Middle School Students Sickened After Ingesting THC Gummies”

This incident occurred close to our pediatric offices and involved four students, just 12 and 13 years old. As pediatricians—and as members of this community—we feel it’s important to talk about what happened and why it matters.

THC is the active compound in marijuana. In edible forms like gummies, the concentration can be quite high. For a child, consuming even a small amount of these products can lead to serious, and sometimes life-threatening, effects.

At this time, it is unclear whether the students in our nearby middle school knew the gummies contained THC, or where they obtained them—whether from a store, a friend, a sibling, or an adult. What we do know is that these products are easy for middle schoolers to access and very easy to mistake for regular candy.


Why are more children at risk for marijuana poisoning now?

A little over a  decade ago, when marijuana was legalized in states like Colorado, the market for THC-infused foods expanded rapidly. Since then, pediatric poisonings related to THC have increased and continue to rise. In states where THC is legal, more widespread adult use has unintentionally increased children’s exposure, as these products are often stored at home.

While many parents are careful to lock away medications, THC edibles are often overlooked. Their packaging is designed to be appealing and can closely resemble popular candy brands. It’s important to recognize that, just like an overdose of prescription medication, ingesting too much THC can be dangerous—and in some cases, fatal.

Even in states where recreational THC use is illegal, THC-related products are still widely available. These products may be unregulated, inconsistently labeled, and easy for children to obtain.

Symptoms of THC intoxication in children can include:

  • Altered mental state or confusion
  • Extreme sleepiness or lethargy
  • Difficulty walking or poor coordination
  • Slurred or slowed speech
  • Excessive vomiting
  • Trouble breathing
  • Loss of consciousness or coma

These symptoms can mimic serious medical conditions such as a stroke or brain injury. Some children require intensive care and life support.

If you suspect your child may have ingested THC, you can call Poison Control at 800-222-1222 for immediate guidance. If your child has trouble breathing, becomes unresponsive, or shows significant changes in mental state, call 911 right away.

How can parents help protect their children from accidental ingestion of THC edibles?

Click to learn more about THC-related compounds, how these products are marketed, and current regulations in Pennsylvania. It’s also important to understand how cannabis can affect the developing brain.

In the photo above, the gummies shown do not contain THC. However, even the most cautious adult would have difficulty telling the difference between candies and THC containing edibles. That’s exactly the concern—and why awareness, prevention, and safe storage are so critical.

Julie Kardos, MD and Naline Lai, MD

©2026 Two Peds in a Pod®


Is it ADHD or something else?

children ADHD
Mr. Rover suddenly came to the realization that every student he had ever taught had ADHD.

Does this sound familiar?

On Monday, your son Robby leaves late for the school bus because he couldn’t find his shoes, then he stopped to fiddle with a Lego model on the way out the door.

On Tuesday, his homework that took you hours to get him to complete the night before never makes it off the kitchen table. 

On Wednesday, he jumps off a five-foot wall at recess “just because” and lands in the nurse’s office.

On Thursday, he comes home tantruming because other kids didn’t want to play with him during recess.

By Friday, you’re sitting at a parent-teacher conference hearing words like impulsive, distracted, underperforming, can’t sit still, and needs constant redirection. A teacher suggests testing for Attention Deficit Hyperactivity Disorder which is better known as ADHD.

If this feels familiar, please know you are not alone. As pediatricians, we’ve sat with many families at this exact moment. It’s natural to feel relief that someone else sees the struggle, and at the same time, worry: What if it’s something else?

That’s such an important question.

What else could it be?

ADHD is common and very real. But several other conditions can look like ADHD—or make attention problems worse. Kids with ADHD are not even necessarily hyperactive. When pediatricians evaluate a child for possible ADHD, we think broadly before landing on a diagnosis.


Sleep is the first place we look. A tired brain can’t focus. Kids who go to bed too late, wake too early, snore loudly, cough at night, or itch from eczema may not be getting enough restorative sleep. Many parents do not realize their kids are up in bed on their tablets or phones, thus cutting into their sleep time. Even mild sleep deprivation can lead to impulsivity and inattention during the day. A rule of thumb is that children who are difficult to wake for school are not getting enough sleep.

Then there are other basics: Can your child see clearly? Can they hear instructions well? Vision and hearing problems are surprisingly common and easily missed.

Learning differences are another piece of the puzzle. Children with dyslexia or other learning disabilities may appear distracted when they’re actually frustrated or overwhelmed. If school feels too hard, it’s easy to “check out.”

Sometimes conditions that impair communication, such as autism, also play a role since difficulty with focus and social interactions can arise in both conditions.

Emotional stress matters, too. Changes at home, family conflict, or bullying can show up as trouble concentrating. Children don’t always tell us they’re worried—but their behavior often does.

Sometimes the “something else” is another medical problem

What looks like “spacing out” could be absence seizures—brief staring spells that interrupt attention. A simple test called an EEG can help rule this out.

We also consider medication side effects. Common antihistamines for allergies, for example, can cause fogginess in some children. And the caffeine in some kids drink at lunch, like soda and iced tea, causes bed time insomnia, which then interferes with falling sleep, which leads to sleep deprivation.

Occasionally, based on other symptoms, we obtain a simple blood test that uncovers something contributing to attention problems, such as anemia (low iron) or thyroid imbalance. In some communities, we also screen for lead exposure, which can affect focus.

And finally, we think about maturity. Younger children in a grade are more likely to be labeled with ADHD than their older classmates. Sometimes what we’re seeing is developmental readiness, not a disorder.

Of course, many children truly do have ADHD. And sometimes they have ADHD plus something else—like needing glasses. We’ve seen children blossom once we address all the pieces of their puzzle.

So if you’re sitting in that conference chair, take a deep breath. An evaluation isn’t a label—it’s information. Our goal isn’t just to name the problem; it’s to understand your child fully so they can more easily learn. 

With careful assessment, the right support, and partnership between parents, teachers, and pediatricians, children like Robby will thrive.

Julie Kardos, MD and Naline Lai, MD

©2026 Two Peds in a Pod®


You’ve Got This: A Gentle Guide to Early Breastfeeding 

Piggies nursing

If you can stick with breastfeeding for the first two weeks, you’ll get past most of the common hurdles. Those early days can feel intense, but a little knowledge (and a lot of grace) goes a long way. Here are some practical, encouraging tips to help you get off to a strong start to early breastfeeding.

Keep at It 

Your baby is your best milk-maker. Every time your baby nurses, their sucking tells your body to make more milk. The more often the breasts are stimulated, the more milk your body produces.


In the hospital, parents are often told to try feeding every 2–3 hours. But babies don’t wear watches. What matters more than the clock is how many times a day your breasts are stimulated. Most babies do well with 8–12 feedings a day.

In those very first feedings, your newborn may feel full after just one teaspoon of colostrum (that early, golden milk). A baby’s stomach is tiny—about the size of their fist—so don’t stress if it feels like you’re not making much at first. That’s completely normal.

When possible, skip the pacifier early on and offer the breast instead. Don’t waste that precious suck!

How Do I Know My Baby Is Getting Enough Milk? 

Diapers are your best clue.

Wet diapers

  • Day 1: at least 1
  • Day 2: at least 2
  • Day 3: at least 3

(The day your baby is born counts as day zero.)

Poopy diapers

  • Day 1: at least 1
  • Day 2: at least 2
  • Day 3: at least 3

Your baby’s doctor will use this information to guide you further when your baby is 3 to 5 days old at their weight check .

Early stools are black and sticky (called meconium). As breast milk moves through, poop changes to a mustard-like consistency. Think anything from liquid yellow ballpark mustard to seedy Dijon—surprisingly varied, all normal.

It can feel like every feeding leads to a diaper change—and often, it does!

What About Weight Loss? 

All babies lose some weight after birth.

This early weight loss is expected. However, babies should not lose more than 10–12% of their birth weight and should regain it by 2–3 weeks of age. Your pediatrician may want to check weight every few days early on to make sure your baby is on track.

A Word About Positioning 

“Proper positioning is key,” says our favorite experienced lactation consultant, Maria Frankenfield. Her top tips:

  • Bring the baby to you—don’t lean your breast down toward your baby. You will likely need a pillow or two to bring  your baby up to breast-level when you sit down to breastfeed.
  • Listen for swallowing, not just sucking.
  • Some brief discomfort at latch-on is okay; ongoing pain is not.
  • Ask for help! Breastfeeding is natural—but it’s also a learned skill.

Try different positions and see what feels best. If one area of your breast feels extra full or tender, aim your baby’s chin toward that spot to help drain it more efficiently, even if it feels a little awkward..

Fast Food or Fine Dining? 

Some babies nurse efficiently for 10 minutes. Others want a leisurely 45-minute meal. Most of the milk is transferred in the first 7–8 minutes of vigorous, active feeding on each breast.

If your baby starts drifting off to sleep while feeding:

  • Lay them against you skin-to-skin
  • Strip them down to a diaper
  • Try gentle stimulation (yes, Dr. Kardos remembers using a cool washcloth on her baby’s foot!)

After about 8–10 minutes on one side, you can switch breasts. If your baby is sleepy before feeding the second breast, try holding your baby upright to burp, pass gas, or—very possibly—poop.

Once your milk is fully in, which can take up to a week, many babies nurse 10–15 minutes per side. We think that feeding both breasts at each meal helps to ensure they get the most milk for their time feeding.

And remember: mom’s kitchen closes for at least an hour after feeding
You are not a pacifier!

Every Baby Is Different 🌱

If your baby gains weight well feeding from just one breast per session, or longer feeds work for you without pain or exhaustion—carry on! Your pediatrician will help guide you on what works for your baby and help with any pumping or supplementation needs. 

One last piece of advice:  If visitors to your home  aren’t willing to do your dishes or help you in any practical way, they don’t stay. This is your time to rest, recover, and practice breastfeeding.

 Helpful websites:

To find a lactation consultant near you see the International Lactation Consultant Association

For more tips on getting started with breastfeeding:  The Children’s Hospital of Philadelphia- breastfeeding tips for beginners

For more practical tips on all things breast feeding related including pumping: Nursing Mother’s Advisory Council  

For personalized virtual help any time of day or night: pacify.com/PDPH

For general breast feeding information and support: La Leche League International 

Julie Kardos, MD and Naline Lai, MD

With input from Maria Frankenfield, MA, BSN, RN, IBCLC

©2026 Two Peds in a Pod®


Why do babies cry?

why do babies cry? Crying emoji and baffled mom

Why do babies cry? In short, infants cry to communicate. Remember, babies cannot talk. They can’t even smile back at you until around six weeks of age.

Dr. Kardos recently welcomed her first grandbaby into the world, so we revisit our baby posts with a fresh eye. Here is the first of many!

The long and short of it is that babies cry when they…

  • Are tired.
  • Are hungry.
  • Feel too cold.
  • Feel too hot.
  • Need to be changed –Dr. Kardos never really believed this reason before she had her twins. Her firstborn couldn’t have cared less if he was wet and could nap right through a really poopy diaper. Then she had her twins. She was amazed that their crying stopped if she changed the tiniest bit of poop or a wet diaper. Go figure. As Dr. Lai says, “different kids are different.”
  • Are bored. Try swapping out the white noise and cue up some hip-hop or K-pop instead. Maybe they want a car ride. Another option: try moving them to another room in the house for a simple change of scenery.
  • Feel pain. Look for a piece of hair wrapped around a finger or toe. Make sure they are not out-growing the elastic wrist or ankle band on their clothing. Dr. Lai’s second born is a young adult but there is still a faint mark on her ankle from tight elastic that only a mom would notice.
  • If the crying is worse in a well-lit room, their eye appears red and irritated, or there are scratch marks next to their eye, your baby may have scratched their eye (corneal abrasion). Call your pediatrician if you suspect this.
  • Need to be swaddled. Remember a fetus spends the last trimester squished inside of their mom. Discovering their own randomly flailing arms and legs can be disconcerting to a newborn.
  • Need to be UN-swaddled. Hey, some like the freedom to flail.
  • Need to be rocked/moved. Dr. Lai’s firstborn spent hours tightly wrapped. Her dad held her in a nearly upside down position nicknamed “upside-down-hotdog.” Every evening he paced with her all around the living room.
  • Need to burp. Lay your crying baby down for a minute. Bring them up again to see if you can elicit a burp.
  • Are gassy. Bicycle their legs while on their back. Position them over your shoulder so that their belly presses against you. You’d be gassy too if you couldn’t move very well. The gassy baby is a topic for this entire post– talk to your doctor for other ideas.
  • Are sick. Watch for fever, inability to feed normally, labored breathing, diarrhea or vomiting. Check and see if anything is swollen or not moving. Listen to the cry. Is it weak and whimper-like (sick) or is it loud and strong (not so sick)? Do not hesitate to check with your pediatrician. Fever in a baby younger than eight weeks old is considered 100.4 degrees F or higher measured rectally. A feverish newborn needs immediate medical attention.


What if you’re certain that the temperature in the room is moderate, you recently changed the diaper, and your baby last ate less than an hour ago?

  • Walk outside with your baby– this can be a magic “crying be gone” trick. Fresh air seems to improve a newborn’s mood.
  • Offer a pacifier. Try many different shapes of pacifiers. Marinade a pacifier in breast milk or formula to increase the chance your baby will accept it.
  • Pick them up, dance, or walk around the house with them. You can’t spoil a newborn.
  • Vacuum your house. Weird, but it can work like a charm. Place your baby in a baby frontal backpack or in a sling while cleaning.
  • Try another feeding, maybe they’re having a growth spurt.
  • When all else fails, try putting them down in the crib in a darkened room. Crying can result from overstimulation. Wait a minute or two. They may self-settle and go to sleep. If not, pick them up again. The act of rescuing may stop the wailing.
  • If mommy or daddy is crying at this point, call your own mom or dad or call a close friend. Your baby knows your voice and hearing you speak calmly to another adult could lull your baby into contentment.
  • Call your child’s pediatrician and review signs of illness.

If you feel anger and resentment toward your crying baby, just put them down in a safe place such as their crib, walk outside, and count to ten. It is impossible to think rationally when you are angry, and you may hurt your child in order to stop your frustration. Seek counseling if these feelings continue.

Now for the light at the end of the newborn parenting tunnel: the peak age when babies cry is six weeks old. At that point, infants can cry for up to THREE HOURS per day. Some fussy babies cry MORE than three hours per day. (Can you believe people actually studied this? Dr. Kardos always found it amusing that Dr. Lai won a prize in medical school for a paper on the history of colic/crying babies). By three months of age, babies cry less often.

While most crying babies are healthy babies and just need to find their perfect upside-down-hot-dog position, an inability to soothe your baby can be a sign of illness. Never hesitate to call your baby’s doctor if your baby is inconsolable, and don’t listen to the people who say, “Why do babies cry?…They just do.”

Julie Kardos, MD and Naline Lai, MD
©2025 Two Peds in a Pod®


Gift Ideas for Newborns: Recommendations from Pediatricians

Baby in a bath under a water shower to highlight gift ideas for newborns

Looking for gift ideas for baby showers or baby namings beyond cute baby outfits and big items? Dr. Kardos welcomes a little one into her family soon so we thought we’d give you some pediatrician-inspired ideas. These gifts support the essentials of what little (and big) people need to do: eat, sleep, pee, poop, love, and learn.

EAT

Pick up breast pump accessories, bottles and nipples, post-partum doula help, and lactation consultant sessions for the new mom.

Vitamin D supplementation is recommended for all babies, whether breast or formula fed. The dose is 400 IU = 10mcg per day. Ask the pharmacist for help finding these over-the-counter baby vitamins.


Parents eat too. Give a gift certificate to a delivery service such as uber eats or  door dash. A homemade casserole or supply of ground coffee goes a long way. 

SLEEP

Sleep sacks

Colorful swaddles for the colicky baby

Crib or bassinet sheets

AVOID: crib blankets, crib pillows, and weighted sleepers and blankets. Please do not add weight to the baby! All of these products carry a risk  of suffocation and increased risk of Sudden Infant Death Syndrome (SIDS). Avoid crib bumpers and soft plushy devices that could be mis-used as a sleep space for a baby. The only safe place for a baby to sleep is in their own bassinet or crib.

For moms breast feeding in winter: consider pajamas with the shirt made for breast feeding.

For parents: consider giving new bedsheets. Many moms experience sweaty sleep as their body chemistry adjusts from pregnancy to life beyond giving birth. New parents might find themselves changing their own bedsheets more frequently than before. 

PEE and POOP

Diapers- parents will appreciate not having to run out to restock- consider getting size 1 or 2 as newborns outgrow the “newborn” size diapers fairly quickly. Sound like a blase idea to you? Make a diaper cake.

Diaper rash prevention creams- get a white zinc oxide containing cream and something clear like Vaseline petroleum jelly or Aquaphor. 

Simethicone gas drops for a gassy baby 

Wipe warmer: is this a necessity? NO! Just scrunch up the wipe in your hand for a few seconds which warms it up to 98 degrees (body temperature) before using it on the baby. However, if you are buying for new parents who have the essentials, a wipe warmer is a nice “extra.”

LOVE/health:

No pediatrician gift basket would be complete without acetaminophen (Tylenol) for treating pain and fever, but remind parents not to give acetaminophen to babies younger than 8 weeks (2 months) of age before checking in with the baby’s pediatrician.

Medication dosing syringe-a 5ml syringe is the most practical size.

Nasal saline – newborns often have something called Nasal Congestion of the Newborn. New parents should not overdo suctioning. Too much suction can cause irritation instead of helping a baby. 

Bulb suction syringe – see above, helps remove mucus from baby’s nose and mouth to help feedings go better.

Easy-to-read thermometer- we suggest a simple digital thermometer that can be used rectally- the proper way to check for a fever in a newborn- and also in the armpit to use when the baby is 8 weeks of age or older.

Nail clippers and nail files- babies grow quickly and so do their nails!

Baby gum/tooth brush cleaner. You could also use a simple wash cloth for this purpose, but gum/tooth cleaners are fun to have. 

Pacifiers- find several shapes and brands as it can be difficult to predict which kind the newborn will like. Remember, some babies just don’t like any of them, and that’s ok too.

LEARN:

Books, books, books! Parents can begin reading to their babies as newborns. Small board books with bright colors are a great start. Click here for our developmental guide to reading to a child.

Contribute to a 529 plan (education investment account) if parents have opened one for their child’s future education. This money can be used for K through 12 private school tuition, trade schools, college, and beyond.

For parents: the following are a few of our recommendations for educating parents about newborns:

Caring for your baby and young child, 8th edition, birth through age 5: American Academy of Pediatrics Drs. Tanya Altmann and David Hill

Heading Home With your Newborn: From Birth to Reality, Drs. Laura Jana and Jennifer Shu-5th edition

Baby 411– Dr. Ari Brown

The Ultimate Baby Book for New Dads: 100 Ways to Care for Your Baby in Their First Year– Dr. Roy Benaroch 

Julie Kardos, MD and Naline Lai, MD
©2025 Two Peds in a Pod®


If your child is afraid of vaccines: take the sting out

As Drs. Kardos and Lai can attest, even a pediatrician’s child does not always approach the prospect of an immunization with a grin on their face. When Dr. Lai’s daughter was two years old, she thanked her nurse for her flu vaccine by giving her a surprise punch. Here are ways you can take away the sting of a needle if your child is afraid of vaccines.

Set the stage 

Your child looks to you for clues on how to act. If mommy and daddy are trembling in the corner of the room, it will be difficult to convince your child that the immunization is “no big deal.” Do avoid a weeks-long build up. Simply announce to your child right before you leave to get the immunization, ”We are going to get an immunization to protect you from getting sick.”


Avoid the apology 

Avoid saying “I’m sorry.” Say instead, ”Even if this is tough, I am happy that this will protect you.”

Never lie

 If your kid asks “Will it hurt?” say “Less than if I pinch you.”

Watch your word choice. 

Calling an immunization “a shot” or “a needle” conjures up negative images. Avoid negative statements about injected vaccines. We cringe when parents in the office threaten their children with, “If you don’t behave, then the doctor will give you a shot.” Remember, shots protect against deadly diseases and are not punishments for children.

Kids talk

Be aware that kids, especially those in kindergarten, love to scare each other with tall tales. Ask your child what they have heard about vaccines. Let children know that Johnny’s experience will not be their experience. Clamp down on the older sibling who is teasing their younger one. Instead, enlist the older sibling to help quell any nerves. 

The moment is almost here

Pack some of the tools you use at home to calm your child. A favorite book or stuffy is comforting. Have your child practice breathing slowly in through her nose and blowing out worries through her mouth. For the younger children, bring bubbles or a pin wheel for your child to blow during the immunization. In a pinch, rip off a piece of the exam paper from the table in the room and have your child blow the paper.

The moment is here

Holding something very cold, placing a cold pack on your child’s arm around the area to be vaccinated, or placing a cold pack on the NON-vaccine arm can distract your child’s brain from feeling the pain of an injection. Some children prefer to look at the vaccination process, while others prefer to look away. Either way is fine. 

Tell your child to count backwards from 10 

It will be over before your child says the number seven.

Have as much direct contact with your child as possible. 

The more surfaces of their body you touch, the less your child’s brain will focus on the injection. By touching your child, you are also sending reassuring signals to him. For the younger child, if he is on the exam table, stay close to his head and hug his arms, or have him on your lap. Holding him firmly will make him feel safe and will prevent him from moving during the injection. Movement causes more pain or even injury.

For the older child and teens, hold their hands. We sometimes see parents of older teens and college students leave the room. However, even big kids may need company during vaccines.

After the drama is over

Have your older child sit quietly for a moment. As the anxiety and tension suddenly fall away, the body sometimes relaxes too suddenly and a child will start to faint. This phenomenon seems to happen most often with the six foot tall stoic teenage boys, but we’ve also seen teen girls and some younger kids get a bit light-headed. If your child becomes pale (or green), have them lie down for a few minutes until they feel better.

Compliment your child

Remind them that their vaccine will keep them from getting severely sick and allow them to see their friends, play their sports, and attend school.

For more tips click here.  

Someday all immunizations will be beamed painlessly into children via telepathy. Until then, we have no advice on how to take the sting away from the punch of a two year old.

Naline Lai, MD and Julie Kardos, MD
©2025 Two Peds in a Pod® revised from 2014


Back to School Health Tips

girl raising hand inside the classroom
Photo by Anastasia Shuraeva on Pexels.com

Whether your child is starting preschool or their last year of high school, use our back to school health tips to start strong:

Sleep

Even if school started for your child, you have time to change their summer sleep schedule. You can adjust it to fit their school year sleep needs.

Take a week or so to gradually dial back their bedtime. Otherwise, they will spend the first week of school jet lagged. The right amount of sleep for your child is whatever amount it takes them to wake naturally or to awaken with minimal prompting . Some kids need 8- 9 hours of sleep, others require 11-12 hours.

Beds are for sleeping only: no playing, studying, phone scrolling, or completing homework in bed. Teach them to “let go” of the day and associate their bed with drifting off to sleep.

Make sure kids of all ages get some exercise, preferably outside, to ward off insomnia at bedtime. On the other hand, exercise too close to bedtime will wind a child up.


For kids who drink coffee, tea, soda or any caffeine containing drinks- avoid these beverages any later than noon. Caffeine can last in the body for up to 24 hours and interferes with sleep.

Visit the bathroom

We know many kids who “hold it” all day in school, despite what we otherwise advise. Remind your children to stop by the potty at least once during the school day. If they claim they don’t need to urinate, they may be dehydrated. Send them in with a water bottle to school. Dr. Lai is fond of saying “You wouldn’t walk around with a baggie full of pee on the outside. So don’t walk around with one on the inside.”

Eat

Pack healthy snacks. Remind your kids that candy has no nutritional value.

Instead of only packing carbohydrates, try giving sliced carrots/celery/peppers and supply hummus, peanut butter, or cream cheese for dipping. Consider packing apple or pear slices along with nut butters or a slice of cheese.

Milk can be a good drink to send along with snacks-even if your child does not eat, they will get some protein as well as carbs from the milk.

Give your child enough time to eat breakfast in the morning. Pack a well balanced lunch, and offer the above snacks after school in addition to packing them for the school day.

Immunize

Flu shots are available by late August/early September each year and some pharmacies already carry them. New this year, some health insurance companies will allow parents to administer the nasal FluMist vaccine at home to their children-ask your pediatrician if your child medically qualifies for this. Otherwise, take them to their pediatrician, school health clinic, or local pharmacy for their annual flu vaccine.

Covid vaccines are safe and effective for children. They reduce the chance of severe Covid complications that would require hospitalization, reduce death from Covid, and also prevent long-Covid symptoms such as months of cough and/or fatigue. The American Academy of Pediatrics (AAP) recommends Covid vaccines for all children this year if they have never had one.

Be sure all of their vaccines are up to date. These include vaccines that prevent meningitis, pneumonia, whooping cough (the “100 day cough,”) measles, mumps (can cause sterility and deafness), and polio.

Stock of up these items to help your child if they get a back-to-school cold:
Honey, nasal saline, tylenol or ibuprofen

And just in case, remind yourself of what to do if the boogers begin to flow by reading our “back-to-school cold” post.

Have a wonderful school year!

Julie Kardos, MD and Naline Lai, MD
©2025 Two Peds in a Pod®





